Orthopedic Medical Billing Guide: Challenges and Strategies for RCM Teams
Discover how medical billing for orthopedic practices works, the key challenges involved, and strategies RCM teams can use to reduce denials and boost revenue.
Published on:
October 4, 2025
Updated on:
September 1, 2026


Key Takeaways:
• Orthopedic billing is among the most complex specialties — multi-step surgeries, implants (HCPCS), 90-day global periods, and CPT/ICD/payer rules that change every year.
• Most denials trace to documentation gaps, modifier misuse (25, 59, 50, 58, 78), NCCI bundling, and missing prior authorizations.
• Undercoding is the quiet twin of denials — missed procedures in long op notes, unbilled implants, and downcoded E/M leak six figures at scale.
• Strong orthopedic RCM tracks clean-claim rate, denial rate, days in A/R, and net collection rate against MGMA benchmarks.
• Self-learning autonomous AI medical coding software such as CombineHealth reads the operative note, applies payer-specific rules, explains every code for audit defense, and learns from denials to reduce them.
Most revenue cycle teams know orthopedic medical billing is complex. Surgeries often involve multiple procedures, devices, and long recovery windows that stretch across global periods.
But the way RCM teams work is shifting. Fast.
New CPT and ICD-10 updates are released each year, payers apply their own ever-changing rules, and prior authorizations add another layer of delay. Billing teams are expected to juggle documentation, coding, claim edits, and appeals—all while keeping up with compliance standards that move faster than most workflows can handle.
Add to that the rise of high-cost implants and payer scrutiny on modifiers, and orthopedic billing requires more than just “getting the codes right.” It demands new strategies, smarter tools, and a more proactive approach to managing the revenue cycle.
This guide explores the biggest challenges in orthopedic medical billing today and the strategies RCM teams can use to stay compliant, reduce denials, and protect revenue.
What Is Orthopedic Medical Billing?
Orthopedic medical billing is the process of converting the specialized care orthopedic providers deliver into the standardized codes and claims insurers require for reimbursement. It bridges clinical documentation and financial accuracy, ensuring that every procedure, device, and follow-up visit is properly recorded, coded, and paid for.
An Overview of the Orthopedic RCM Workflow
The orthopedic revenue cycle management (RCM) workflow involves the following steps:
- Patient Registration & Insurance Verification: Eligibility checks confirm that coverage is active and that orthopedic services, such as imaging or surgery, are included in the patient’s plan.
- Clinical Documentation: Providers record the clinical encounter, including exam findings, imaging, surgical details, and any implants used.
- Coding: Coders then assign CPT, ICD-10, and HCPCS codes, adding modifiers when needed. In orthopedics, getting laterality (right vs. left), encounter type, and implant details correct is crucial for clean claims.
- Billing and Claim Submission: Once coded, the visit is converted into a claim. Before it is sent to the payer, billing systems apply edits and scrubbers to catch errors against payer rules and NCCI guidelines.
- Denial Management and payment posting: After payers process the claim, payments are posted to patient accounts. Any denials are reviewed, corrected, and appealed if appropriate.
CombineHealth runs across this entire workflow rather than bolting onto one step. It reads the documentation, assigns CPT, ICD-10, and HCPCS codes with the right modifiers and laterality, applies payer rules and NCCI edits before the claim is submitted, and turns each denial into feedback that sharpens the next claim. Because the platform is autonomous and self-learning, routine encounters move without manual coding, and every decision it makes is explainable back to the note.

What Makes Orthopedic Medical Billing Hard?

Orthopedic billing is among the most difficult specialties because it blends high-cost procedures with some of the most detailed coding rules in healthcare. Here are the most common factors that make billing for orthopedics so challenging:
- High-complexity, anatomy-specific coding — precise site, laterality, and procedure across CPT/ICD-10/HCPCS.
- 90-day global surgical periods — pre- and post-op bundled into one payment; careful tracking prevents duplicate-billing flags.
- Dense modifier rules — 25, 50, 58, 59, 78, 79, RT/LT, plus assistant-at-surgery.
- NCCI bundling edits — payers restrict separate billing for services included in a primary procedure.
- Prior authorization — high-cost imaging (MRI) and outpatient surgeries (TKA, THA, spinal fusion) require upfront auth.
- Diverse service mix — office visits, injections, casting, fracture care, DME, and physical therapy alongside major joint replacements.
- Constant change — annual CPT/ICD updates plus payer-specific policies that shift mid-year.
This is precisely the complexity CombineHealth was built for. It reads the full operative note and resolves the details orthopedic claims turn on—site and laterality, which steps are separately billable versus bundled into the surgical package, the right modifier for the scenario, and the implant or HCPCS device that would otherwise go unbilled—then applies each payer's rules to the result. The hard part of orthopedic coding is exactly what the platform automates.
Orthopedic Medical Billing Guidelines in 2026
New updates in orthopedic coding and billing guidelines introduce changes to coding, bundling, and device documentation that directly impact reimbursement. Here are some updates you should know about:
- CPT 2026 (AMA, eff. Jan 1, 2026): 418 changes — 288 new, 84 deleted, 46 revised. Ortho highlights: deletions 27445/27468; new 27458/27713 (osteotomy + lengthening device), 64728 (percutaneous median-nerve decompression), 1003T (first CMC total joint arthroplasty); revised total-joint-revision and SI-joint guidance.
- ICD-10-CM FY2026 (CMS, eff. Oct 1, 2025) — match the diagnosis set to the date of service.
- Telemedicine 98000–98016: Medicare pays only 98016; use 99202–99215 + telehealth POS/modifier for Medicare.
- NCCI Policy Manual 2025: The manual refines bundling/unbundling rules and highlights modifier protocols. Orthopedic billing teams should pay special attention to shoulder and knee surgery edits and correct the use of modifiers 59, XS, LT, and RT.
- LCD & Policy Article Revisions: Medicare contractors introduced new HCPCS codes and coverage criteria for orthopedic supports like ankle-foot and knee orthoses. Documentation must now reflect device specifics to ensure coverage.
Keeping pace with all of this by hand is the problem CombineHealth's payer intelligence removes. The platform continuously incorporates the latest AMA CPT, ICD-10-CM, and HCPCS changes—including the 2026 orthopedic updates and quarterly NCCI revisions—and learns each payer's evolving policies from real claim outcomes. Coding is validated against the rules in force on the date of service, not the rules a coder last had time to study.
Essential Codes for Orthopedic Medical Billing
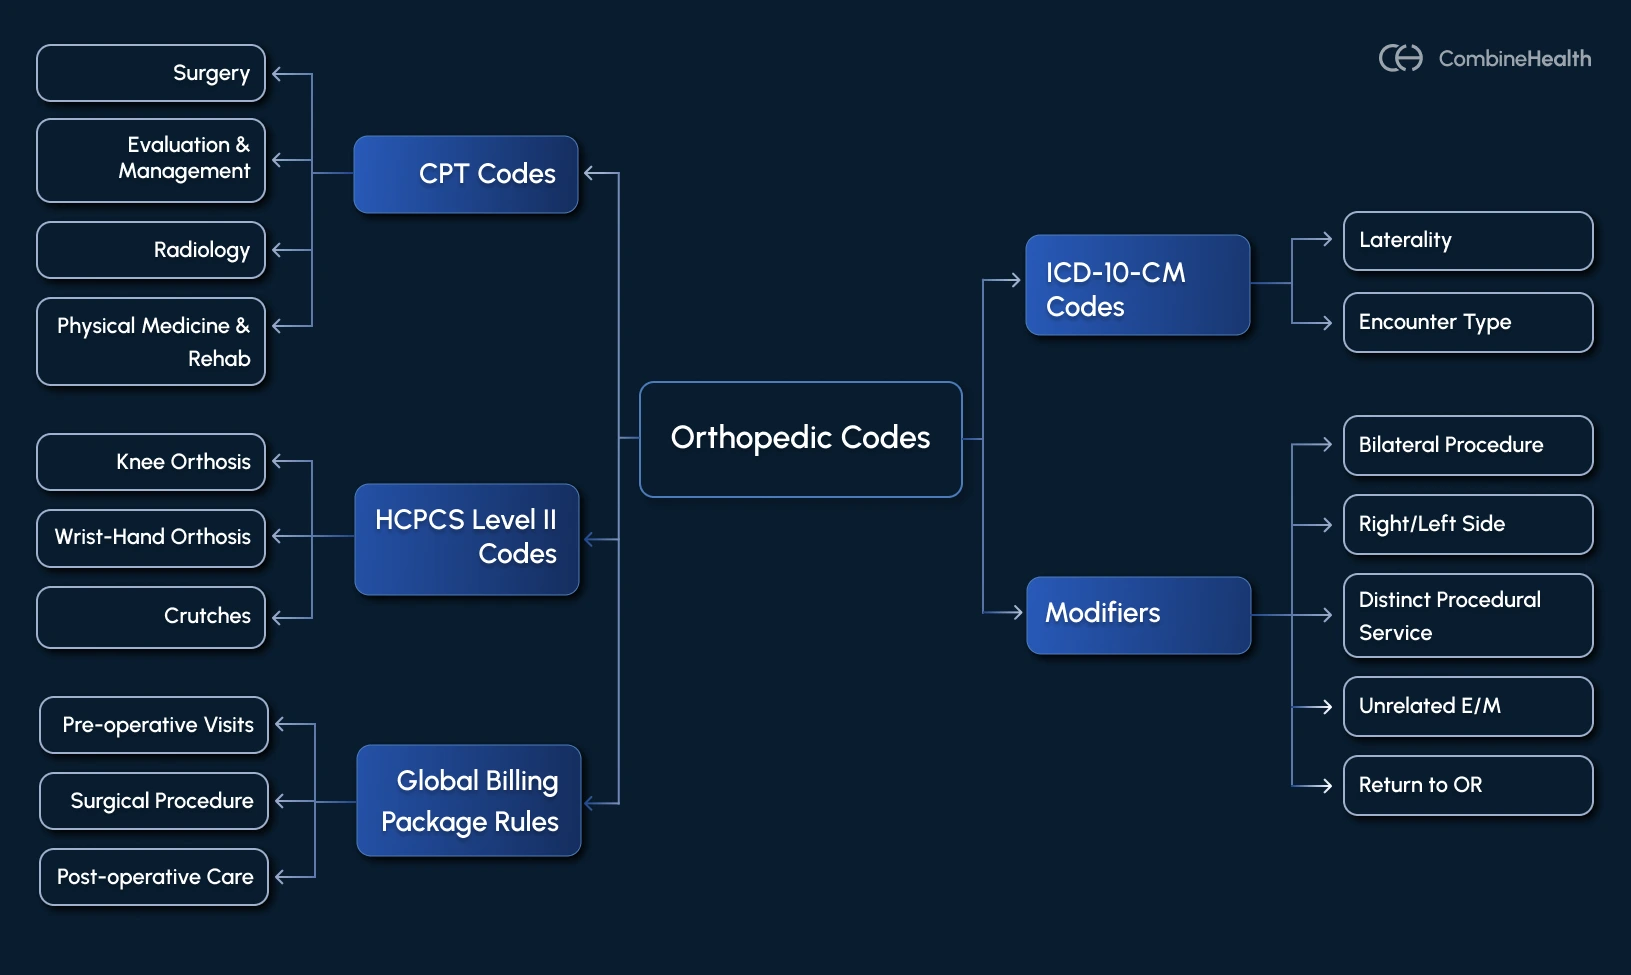
Orthopedic practices must be fluent in CPT, ICD-10, HCPCS/HCPCS II, and supply/implant codes. Below is a deeper map of what matters and how to organize your coding infrastructure:
1. CPT Codes: Services and Procedures
Current Procedural Terminology (CPT) codes describe the medical services and procedures provided. In orthopedics, the most commonly used categories include:
- Evaluation & Management (E/M)—99201–99499: These codes cover office visits, consults, and follow-ups. Correct selection depends on history, exam, and medical decision-making. With the 2025 E/M guidelines, documentation must clearly justify complexity, not just time spent.
- Surgery—10021–69990: This is the largest section for orthopedics, covering everything from fracture repairs to joint replacements.
- Radiology—70100–79999: Imaging is central to orthopedic diagnosis and follow-up. Codes in this category apply to X-rays, MRIs, CT scans, and ultrasound guidance for procedures.
- Physical Medicine & Rehab—97000 series: Post-op care often includes therapy services. These codes ensure practices capture revenue for rehabilitation and ongoing musculoskeletal management.
The table below highlights some common CPT codes in orthopedic billing:
2. ICD-10-CM Codes: Diagnosis and Specificity
ICD-10 diagnosis codes explain why the service was performed. In orthopedics, denials often result from vague or incomplete coding. The 2025 ICD-10 updates introduced additional musculoskeletal and fracture-related codes.
Here are some points to consider:
- Laterality is required: Always code whether the condition affects the right, left, or bilateral site.
- Encounter type matters: Initial encounter (A), subsequent encounter (D), or sequela (S) must be noted.
The table below highlights some common ICD-10 codes used when billing for orthopedic:
3. HCPCS Level II Codes: Devices and Implants
Orthopedic billing often involves high-value supplies, implants, and durable medical equipment (DME). HCPCS Level II codes capture these items when they are not bundled into a CPT procedure.
The table below highlights some common orthopedic HCPCS examples:
4. Modifiers
Correct use of modifiers ensures payers process claims accurately. For orthopedics, some of the most important modifiers are highlighted in the table below:
5. Global Billing Package Rules
A global billing package (also called the global surgical package) is the set of rules payers use to decide what’s included in the payment for a surgery and what can be billed separately.
Think of it like a “bundle deal.” When you bill for an orthopedic surgery (say a hip replacement), the payer isn’t just paying for the operation itself—they’re also paying for the standard care that normally comes before and after that surgery.
Medicare (CMS) sets the official framework through the Medicare Physician Fee Schedule and the Medicare Claims Processing Manual.
So, what’s included in the global package:
- Pre-operative visits (after the decision for surgery is made).
- The surgical procedure itself.
- Typical post-op care, such as wound checks and routine follow-up visits, for up to 90 days after major procedures (10 days for minor surgeries).
Not everything is bundled. If care goes beyond what’s normally included, you can (and should) bill it, but only with the right modifier and documentation:
- Modifier 24: Use for an unrelated E/M service during the global period (example: a patient returns with a new hip pain unrelated to their knee replacement).
- Modifier 78: Use when a patient needs to return to the OR during the global period for a complication related to the original surgery.
- Modifier 79: Use for an unrelated procedure or surgery performed during the global period.
6. Medical Coding by Service Type
Modifier and global-period calls like these are where CombineHealth's explainability earns its keep. When it applies a 24, 78, or 79—or a 25, 59, or 50—it links the choice to the specific note language and payer rule that justify it, so the high-scrutiny modifiers that draw payer audits are defensible rather than black-box outputs. The reasoning is captured with the code, ready for an audit or appeal.
Orthopedic Medical Billing Mistakes That Often Cause Denial
Even the most experienced billing teams can slip up when handling orthopedic claims. Understanding the most common mistakes upfront helps orthopedic RCM teams prevent them before claims ever reach the payer.
Mistake 1: Unbundling of Services
Unbundling happens when you bill separate codes for things a payer considers part of a single, inclusive service. In orthopedics, this is a live problem because many surgeries contain multiple steps, supplies, and post-op care that payers treat as packaged into the primary procedure.
When a claim tries to extract one of those pieces, it often trips automatic NCCI or MUE edits and gets denied.
So, how to avoid this?
- Add payer-specific NCCI and MUE rules to your pre-submission scrubber so bundled items are flagged before claims go out.
- Maintain a local “bundle vs separate” rulebook for your top 50 CPTs and push those rules to both clinical staff and coders.
- Train perioperative staff and coders on your bundled scenarios so charge capture is consistent.
This is a check CombineHealth runs before the claim ever leaves your system. It evaluates each code combination against payer-specific NCCI and MUE edits, flags bundled items that shouldn't be billed separately, and shows the rule behind the flag—so the unbundling denial is prevented at coding, not discovered on the remittance. The "bundle vs. separate" logic applies consistently across every provider instead of living in one coder's head.
Mistake 2: Inappropriate E/M Plus Procedure Billing for Orthopedic
An E/M code plus a procedure code can be billed together when the clinician provides both evaluation or management and a procedure during the same encounter. However, it’s only allowed when the E/M is a distinct and separately identifiable service from the procedure.
Payers deny these claims when the chart does not clearly show two different services happened, or when the documentation does not show separate medical decision making for the E/M.
Let’s clear this up using these examples:
Scenario: New problem -> evaluation + plan, then a procedure
Patient has new right knee instability. You evaluate, decide to order an MRI, and start PT. Later, on the same visit, you aspirate the knee.
Documentation to use: “E/M for new right knee instability—MRI ordered and PT initiated. Therapeutic aspiration performed later; E/M is distinct.”
Scenario: Visit is only for the procedure
Patient comes in for a scheduled knee aspiration. Note documents only the procedure and immediate tolerance.
Documentation to use (if truly separate, it would need more): “Procedure visit only—aspiration performed; no separate E/M.”
Mistake 3: Missing medical necessity, image-guidance proof, or Prior Auth for Injections
Payers commonly deny injection claims when the chart lacks evidence of prior conservative treatment (example: physical therapy), missing proof that image guidance was used when billed, or no prior authorization was obtained. These gaps make the service look nonessential or bundled with another visit.
Mistake 4: Modifier Misuse
Applying a modifier without documentation proving the service was truly separate invites payer denials because it lacks the clinical justification required for separate payment. For example, showing a different anatomic site, a distinct incision, or a separate encounter in the documentation.
Here’s why payers deny it:
Payers and automated edits treat some modifiers as a way to bypass bundling rules. If the chart doesn’t show the clinical fact that justifies the modifier, the claim is flagged and denied.
Because CombineHealth ties every modifier to the documented clinical fact that supports it—a distinct anatomic site, a separate incision, a separately identifiable encounter—it won't append a modifier the note doesn't justify, and it flags the documentation gap when the clinical fact is missing. That's the difference between a modifier that survives an automated edit and one that triggers a denial or an audit.
Is Your Orthopedic Practice Undercoding?
Denials are visible; undercoding is quiet and often costlier. Orthopedic revenue leaks through billable procedures missed in long operative notes, unbilled implants and HCPCS devices, missing modifiers (59, 50, RT/LT), and downcoded E/M. With AAOS putting orthopedic denials around 10–15% and MGMA benchmarking a healthy net collection rate at 95–98%, even a few points of gap is six figures at scale.
Because these errors are systematic, they're findable: compare each provider's code and E/M distribution against acuity and peers, and audit every chart — not a 10% sample — for missed charges and the documentation behind them before claims go out. When one surgeon reimburses less than peers for similar cases, coding is usually the reason.
Auditing every chart(not a 10% sample) is exactly what an autonomous platform makes feasible.
CombineHealth reviews the full operative note on every encounter, surfaces the billable procedures buried in long op notes, the unbilled implants, and the downcoded E/M levels, and compares coding patterns across providers to show where revenue is leaking. In one high-volume deployment it identified five times more documentation gaps than the prior manual workflow—the kind of missed detail that, at orthopedic volumes, adds up to six figures.
How Do You Reduce Coding-Related Denials in Orthopedics?
Most orthopedic denials are preventable at the source. Five moves cut them:
- Complete documentation — laterality, medical necessity, and operative detail that supports every code and modifier.
- Code to each payer's rules — apply LCDs/NCDs and payer-specific edits before submission, not after the denial.
- Pre-bill review — validate coding against the documentation (not just the claim) before it goes out.
- Learn from past denials — categorize denials by payer, code, and reason, and feed the patterns back into coding.
- Catch bundling early — check NCCI edits before billing stacked procedures.
This is where self-learning AI helps most: CombineHealth applies payer-specific rules up front and learns each payer's behavior from real outcomes, so the same avoidable denial doesn't repeat.
Keeping Orthopedic Coding Consistent as You Scale
Two coders can read the same operative note and code it differently, and that variation multiplies across surgeons and locations. As groups grow — or acquire practices — coding drifts and denials climb. The fixes:
- Standardize the logic — one coding rubric (and, ideally, one automated engine) applied across every provider and site.
- Automate the routine — when you can't hire enough specialty coders, automate high-volume routine encounters so coders focus on complex surgical cases.
- Scale without headcount — autonomous coding absorbs volume spikes and new locations without linear hiring.
- Monitor by provider & location — track coding and denial patterns to see exactly where a surgeon or site drifts.
This is the core case for autonomous medical coding. CombineHealth applies one consistent coding logic across every surgeon and location, absorbs volume spikes and newly acquired practices without linear hiring, and continuously incorporates each payer's rules—so coding doesn't drift as the group grows. Its provider- and location-level analytics show exactly where a surgeon or site diverges, turning "coding varies across our practices" from a blind spot into a monitored metric.
Key Performance Indicators (KPIs) for Orthopedic RCM
Here are some critical orthopedic RCM metrics to track and benchmarking guidance:
How can AI help with Orthopedic Medical Billing
The newest orthopedic medical coding tools don't just suggest codes — they code autonomously and learn from payer behavior. CombineHealth (also referred to as Amy AI), a self-learning autonomous medical coding platform, reads the full operative note and generates explainable, billing-ready codes — CPT, ICD-10, HCPCS, modifiers, and E/M — then evaluates every decision against real claim outcomes (denials, downcodes, underpayments) to build payer intelligence that adapts coding per payer.
- Explainable, audit-ready: Every code links to the note section, guideline, and payer rule behind it — so high-scrutiny calls (modifier 25/59, bilateral, assistant-at-surgery) are defensible, not black-box outputs.
- Payer intelligence + always current: It learns each payer's behavior and continuously incorporates the latest AMA CPT, ICD-10-CM, and HCPCS changes — including the 2026 orthopedic updates — so coding stays compliant and denials fall: up to 85% automation, 98%+ accuracy, and up to a 75% reduction in coding-related denials. The same platform extends across the cycle — eligibility, claim scrubbing, A/R follow-up, and appeals.

Top 5 AI Orthopedic Medical Coding Solutions (2026)
For teams evaluating tools, here are five worth a look — see our full Top 10 AI orthopedic coding solutions for the complete comparison.
- CombineHealth — a self-learning autonomous medical coding platform with payer intelligence and explainable, audit-ready coding for operative notes, modifiers, global periods, and HCPCS implants. Best for mid-to-large orthopedic groups and multi-location practices.
- ModMed Orthopedics — an orthopedic-specific EHR suite with embedded workflows and code suggestions. Best for practices wanting an all-in-one specialty EHR.
- Optum Integrity One — enterprise coding-integrity and CDI tooling. Best for large health systems.
- athenaOne — networked EHR/RCM with claim intelligence drawn from a large payer network. Best for practices already on athenahealth.
- DrChrono — cloud EHR with billing for smaller practices. Best for independent or small orthopedic offices.
Transform Orthopedic Billing With Intelligent Automation
Orthopedic medical billing is complex by design, with layered coding rules, global periods, device documentation, and payer edits that rarely stand still.
Looking ahead, the real opportunity is to stop playing catch-up and start building proactive systems that anticipate payer requirements before claims go out the door. With structured processes, up-to-date guidelines, and intelligent automation, orthopedic groups can transform billing from a source of revenue leakage into a steady, reliable part of practice growth.
Ready to see autonomous, self-learning coding on your own orthopedic charts? Book a demo with CombineHealth and see how it adapts to your payers, explains every code, and reduces denials.
FAQs
What is medical billing for orthopedics?
Orthopedic medical billing converts clinical care (from evaluations to surgeries) into standardized insurance claims using CPT, ICD-10, and HCPCS codes. It ensures providers are reimbursed accurately for musculoskeletal treatments, implants, and post-operative care.
Is orthopedic billing hard?
Yes. Orthopedic billing is complex because it involves multiple procedures, detailed documentation, strict modifier rules, global periods, and frequent payer-specific updates.
What are the orthopedic medical billing requirements?
Accurate documentation, correct CPT/ICD-10 coding, proper modifier use, compliance with global package rules, and payer-specific prior authorizations are essential to avoid denials and ensure timely reimbursement.
What is the CPT code for orthopedic services?
Orthopedic services use CPT ranges for E/M (99201–99499), surgery (10021–69990), imaging (70100–79999), and therapy (97000 series), depending on the procedure performed.
What are the most common orthopedic billing and coding errors?
Unbundling services against NCCI edits, misusing modifiers (25, 59, 50), billing an E/M with a procedure without support, missing prior authorizations, and downcoding from incomplete documentation.
How do you code multiple procedures in the same orthopedic surgery?
Report the highest-RVU procedure first, add others with modifier 51, and check NCCI edits for bundling. Distinct procedures at separate sites may unbundle with modifier 59/XS when documented.
When should Modifier 25 be used in orthopedic billing?
When a significant, separately identifiable E/M is performed beyond a procedure's inherent work on the same day — for example, evaluating a new problem alongside a joint injection. Documentation must stand on its own.
How do you bill bilateral orthopedic procedures?
Usually modifier 50 on one line (per payer), or RT/LT on separate lines for payers that require it. Confirm each payer's convention.
Can orthopedic surgeons bill for radiology interpretation?
Yes — the professional component (modifier 26) when the surgeon personally interprets and documents the imaging and it isn't bundled or already read by another provider.
How do you know if your orthopedic practice is undercoding?
Compare each provider's code and E/M distribution to acuity and peers; a low-skewed curve or below-peer reimbursement for similar cases signals undercoding. Auditing every chart confirms missed procedures and modifiers.
Why does one payer deny an orthopedic procedure that others reimburse?
Payers apply different edits and medical-necessity rules to the same code. Payer-specific coding before submission — and a platform that learns each payer's behavior from past outcomes — prevents the repeat denial.
Can AI code orthopedic operative notes, and how much can be automated?
Yes. A self-learning autonomous platform like CombineHealth reads the full operative note and codes CPT, ICD-10, HCPCS, E/M, and modifiers autonomously and explainably, automating up to ~85% of encounters at 98%+ accuracy while surfacing the documentation gaps that would otherwise cause a denial. Every code links back to the note and the payer rule behind it, so the coding is auditable, not a black box.
What should you look for in orthopedic coding software?
Professional + facility coding, support for modifiers/global periods/HCPCS implants, payer-specific rules, explainable audit trails, EHR integration, and the ability to pilot on your own charts measuring denial reduction — not just automation rate.






