Why Autonomous Medical Coding and CDI Must Operate As One Workflow
Learn why autonomous medical coding and CDI must work together to identify documentation gaps, improve coding accuracy, and reduce denial risk.
Published on:
October 13, 2026


Autonomous medical coding and clinical documentation improvement (CDI) should operate as one workflow because a coding system can accurately assign codes from an incomplete record and still miss legitimate, supported revenue or finalize a decision the documentation doesn't fully support.
When CDI runs inside autonomous coding, the platform evaluates documentation sufficiency as it codes: it assigns the codes the record supports, flags missing specificity or evidence as a CDI alert or query before billing, and keeps every decision explainable.
CombineHealth is built this way — self-learning autonomous coding with payer intelligence and AI-powered CDI in one connected workflow — which at a 400-bed hospital helped cut coding-related denials 75% and surface 5× more CDI opportunities.
Medical coding asks, “What does the documentation support?”
Clinical documentation improvement (CDI) asks, “Does the documentation completely and accurately represent the care delivered?”
A connected workflow answers both questions before billing.
The American Health Information Management Association (AHIMA) emphasizes that complete, consistent clinical documentation is essential to accurate coding, quality reporting, and appropriate reimbursement.
Yet autonomous medical coding and CDI are often evaluated as separate functions: one for coding productivity, the other for documentation quality.
The problem is that a coding system can accurately assign codes from an incomplete record and still miss a legitimate billing opportunity.
This is why autonomous medical coding and CDI should operate as one connected workflow rather than separate processes that identify and resolve documentation problems at different stages of the revenue cycle.
What Is the Relationship Between Autonomous Medical Coding and CDI?
Autonomous medical coding assigns codes based on documented clinical evidence, while clinical documentation improvement (CDI) identifies missing, ambiguous, or inconsistent information that may affect those codes. When integrated, CDI evaluates documentation sufficiency during autonomous coding, helping the platform produce complete, accurate, and defensible coding decisions before billing.
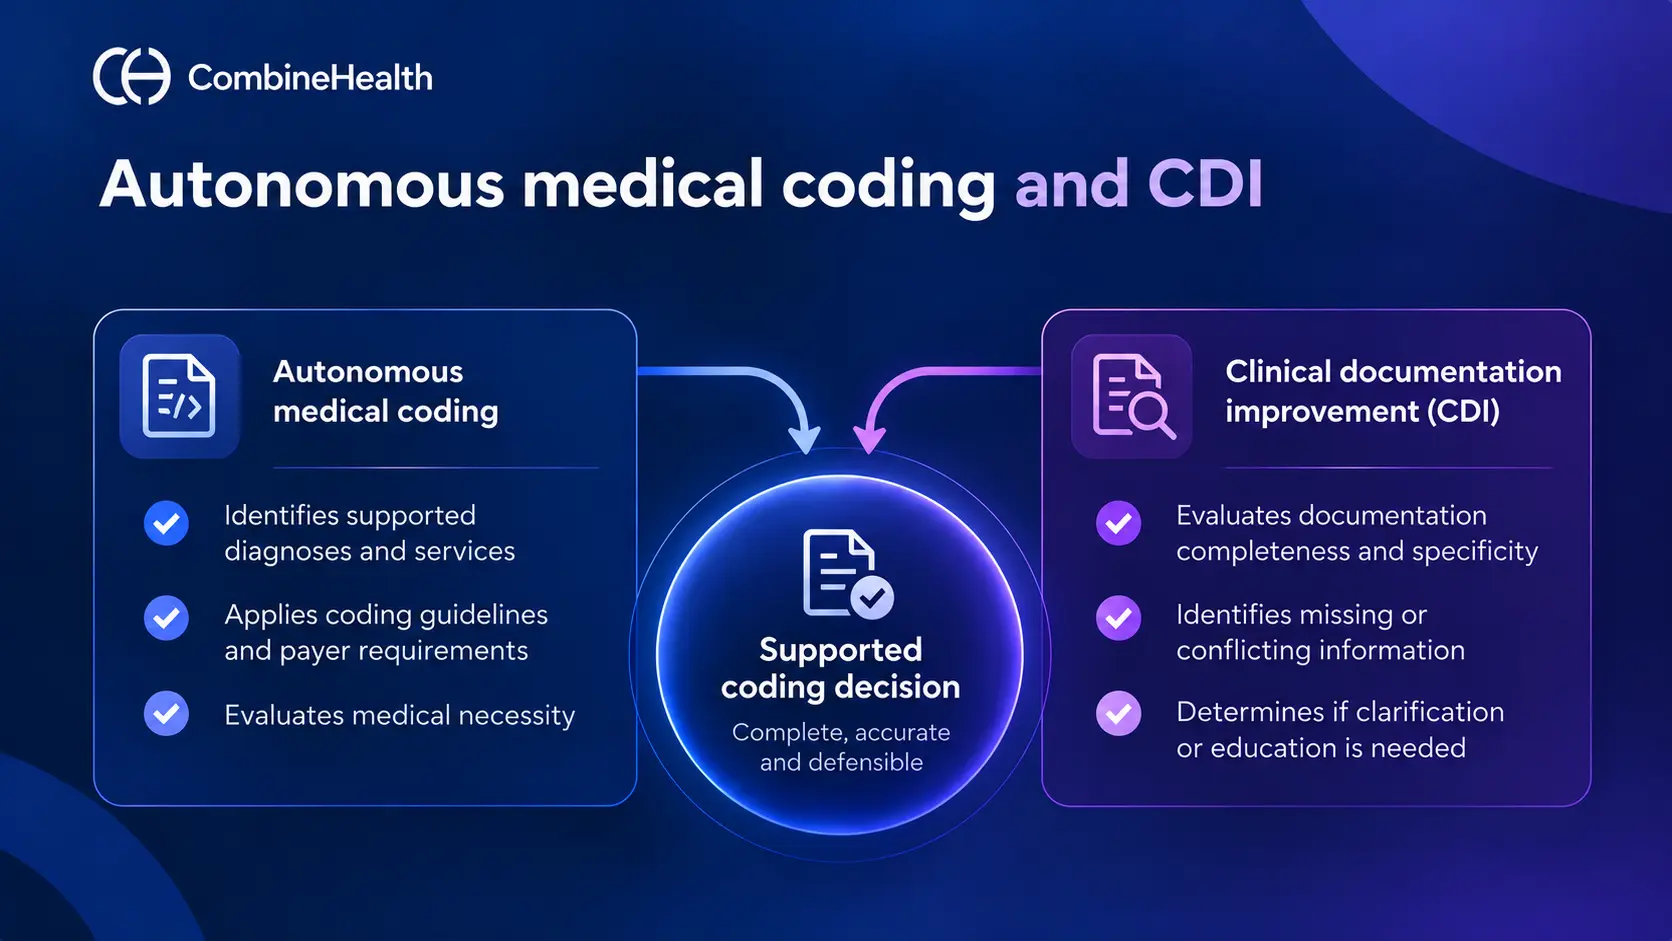
The two functions have distinct but complementary responsibilities:
CombineHealth is built on exactly this integration. Its autonomous coding and AI-powered CDI run as one workflow: as it reads the encounter and assigns codes, it simultaneously evaluates whether the documentation supports them — so both questions above are answered together, before billing, rather than in separate coding and CDI queues.
Why Does Autonomous Medical Coding Need CDI Inside the Workflow?
Autonomous coding needs integrated CDI because missing documentation can affect code specificity, E/M levels, medical necessity, and reimbursement. Identifying these deficiencies during coding helps prevent unsupported decisions, missed coding opportunities, and unnecessary rework.
Three problems make the integration important:
1. Autonomous Coding Cannot Assign Codes Without Supporting Documentation
Autonomous medical coding systems can identify diagnoses and services documented in the clinical record. However, they should not invent missing clinical facts to assign more specific codes.
For example, an orthopedic encounter may document a fracture without the laterality or encounter details required for specific code selection.
Integrated CDI identifies the missing information so the encounter can be evaluated for clarification.
The official ICD-10-CM guidelines require coding based on appropriate provider documentation and applicable classification rules.
This is why CombineHealth evaluates documentation sufficiency as it codes. It assigns the codes the record supports, flags the missing specificity or evidence that would otherwise cause undercoding or an unsupported decision, and does it during coding, not after a denial, so documentation gaps are caught before the encounter is finalized rather than becoming a rework cycle. It never assigns codes the documentation doesn't support.
2. Accurate Coding Can Still Miss Reimbursement Opportunities
A system may correctly code everything documented in an encounter while missing services that were performed but insufficiently documented.
This can contribute to undercoding, incomplete diagnosis specificity, and missed billable services.
Integrated CDI helps identify documentation deficiencies that may affect coding completeness before the encounter reaches billing.
Importantly, the goal is not to increase reimbursement regardless of clinical evidence. Any additional code or service must be supported by accurate documentation and applicable coding guidelines.
3. Separate Coding and CDI Workflows Create Unnecessary Handoffs
When coding and CDI operate independently, a documentation deficiency may be discovered after coding is completed.
The encounter may then require a CDI referral, provider clarification, and recoding.
An integrated workflow evaluates documentation sufficiency during coding, allowing supported encounters to proceed while material deficiencies are routed for clarification.
The benefit is not simply faster coding. It is reducing the risk of incomplete documentation becoming a finalized coding decision.
How Should an Integrated Autonomous Coding and CDI Workflow Work?
A connected autonomous medical coding and CDI workflow should follow six steps:
- Review the complete encounter: Analyze relevant clinical notes, diagnoses, procedures, medications, tests, and supporting records.
- Evaluate coding and documentation: Identify supported diagnoses and services alongside missing, ambiguous, or contradictory information.
- Apply coding and payer requirements: Evaluate official coding guidelines, medical-necessity criteria, and applicable configured payer rules.
- Determine the CDI response: Finalize supported coding, record a documentation alert, or route the encounter for clarification.
- Produce explainable coding output: Link assigned codes and documentation findings to clinical evidence and applicable guidance.
- Analyze claim outcomes: Identify recurring denial and reimbursement patterns that may warrant validated changes to future coding or CDI checks.
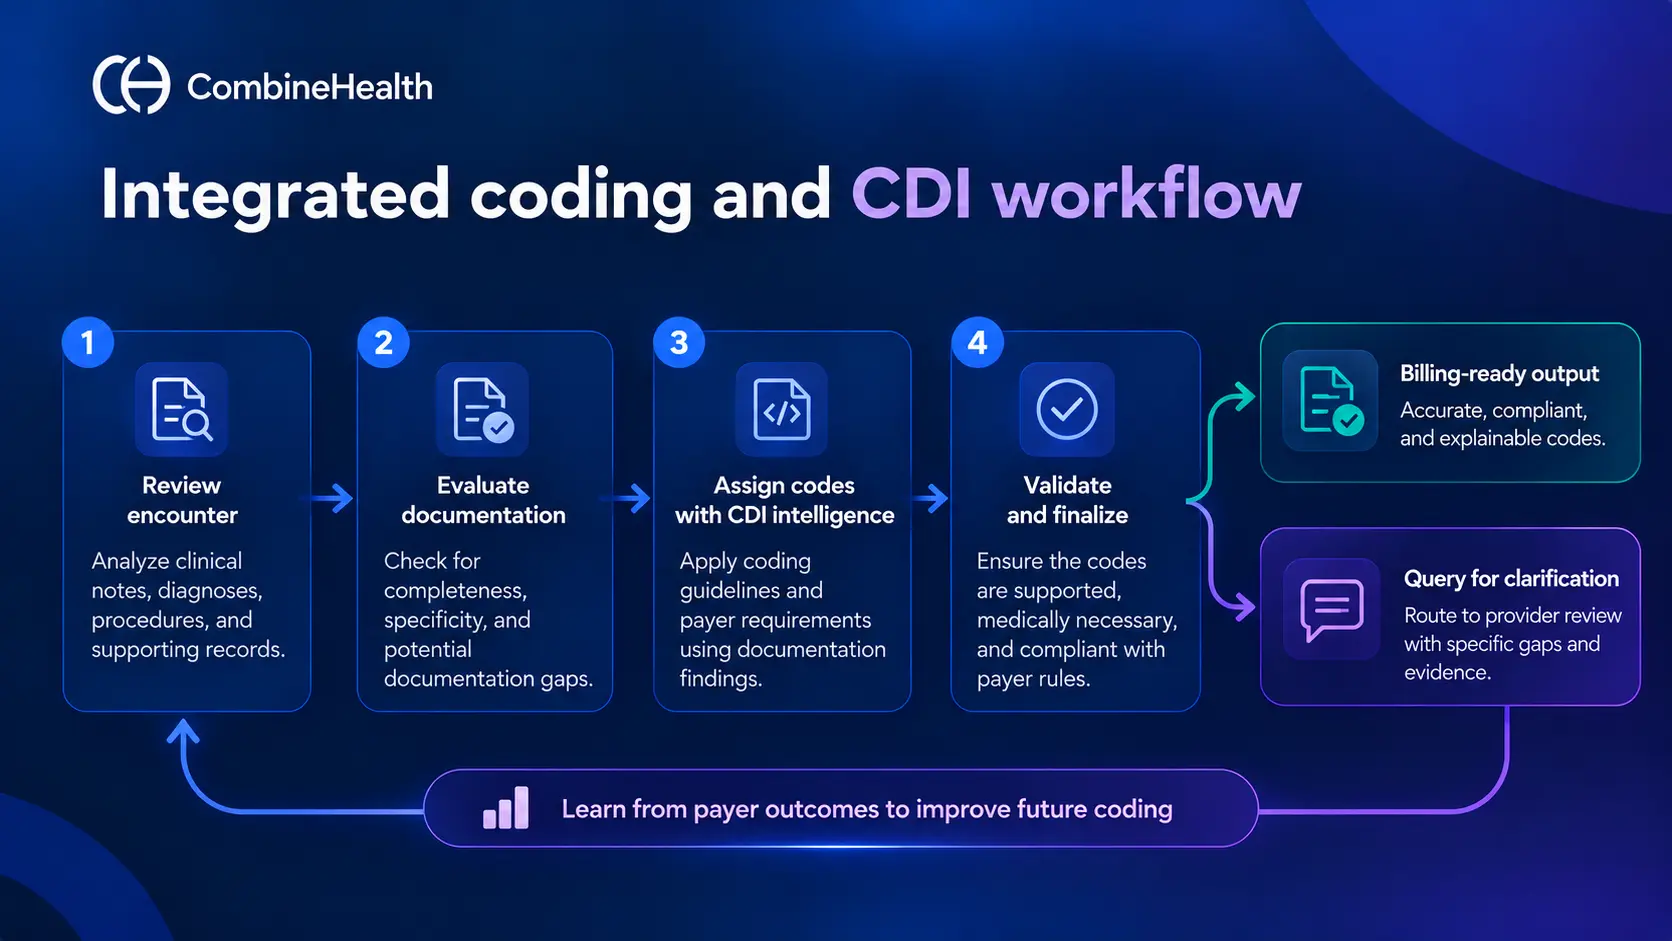
CombineHealth runs this six-step workflow end to end: it reviews the complete encounter, evaluates coding and documentation together, applies coding guidelines and payer requirements, determines the CDI response, produces an explainable output that links codes and documentation findings to the clinical evidence, and learns from downstream claim outcomes to refine future coding and CDI checks.
What Is the Difference Between a CDI Alert and a CDI Query?
A CDI alert identifies a documentation improvement opportunity that does not necessarily require the encounter to be held. A CDI query requests provider clarification when missing or conflicting information may materially affect coding.
CombineHealth applies this distinction as it codes: lower-risk documentation patterns are recorded as CDI alerts for provider education, while missing or conflicting information that materially affects code selection is raised as a CDI query — so routine education doesn't interrupt billing, but a material deficiency is surfaced for clarification before the code is finalized.
When Should an Encounter Be Held for Clarification?
An encounter can proceed when the existing documentation supports a defensible coding decision. It should be considered for clarification when missing or contradictory information could materially affect code selection, medical necessity, or compliance.
An integrated CDI and autonomous medical coding workflow supports two approaches:
Code Now and Educate Later
The platform finalizes supported coding while tracking lower-risk documentation opportunities for future provider education.
This is appropriate when the missing information does not materially affect the current billing decision.
Hold and Query
The encounter is routed for clarification when a material documentation deficiency prevents a defensible coding decision.
This may involve conflicting diagnoses, missing required specificity, or insufficient evidence supporting a reported service.
There should not be one universal threshold for every organization. The appropriate workflow depends on specialty, compliance requirements, and the significance of the documentation gap.
How Does Explainability Connect Autonomous Medical Coding and CDI?
Explainability connects autonomous medical coding and CDI by showing the clinical evidence behind each code, identifying missing documentation, and explaining why an encounter can proceed or requires clarification. This gives coding, CDI, and compliance teams a shared basis for reviewing decisions and resolving disagreements.
An explainable workflow should make the following information accessible:
- Documentation reviewed and clinical evidence identified.
- Codes assigned and applicable coding guidelines.
- E/M rationale, where relevant.
- Documentation deficiencies requiring attention.
- Final coding, alert, or query decision.
- Audit trail of the review.
CombineHealth makes all of this accessible on every encounter. That shared, explainable record is what lets coding, CDI, and compliance teams validate a decision and resolve disagreements — especially when the AI flags a documentation issue that affects the final code.

Explainability is especially important when AI identifies a documentation issue that may affect the final diagnosis or code.
How Does Integrated CDI Help Prevent Coding-Related Denials?
Integrated CDI helps reduce documentation-related denial risk by identifying missing evidence, unsupported services, and medical-necessity gaps before claim submission. When combined with coding and payer-aware validation, it helps organizations address potential billing problems earlier rather than discovering them after adjudication.
Documentation issues can affect whether a claim satisfies applicable coverage and coding requirements.
CombineHealth Customer Results: 400-bed Hospital
In a CombineHealth deployment at a 400-bed hospital, the organization reported the following results within three months:
- 75% fewer coding-related denials
- 5× More CDI opportunities identified
- +4% captured revenue
- 98%+ coding accuracy
The results illustrate why medical coding accuracy, CDI opportunity detection, and financial outcomes should be evaluated together rather than as isolated performance measures.
How Claim Outcomes Improve Autonomous Coding and CDI?
Claim outcomes can reveal recurring coding, documentation, and payer-related problems that were not apparent before submission. A self-learning platform can analyze denials, reimbursements, and underpayments to identify patterns, propose improvements, and apply validated changes to future coding and CDI checks.
A connected feedback process should:
- Identify recurring denial or reimbursement patterns.
- Determine whether the cause involves coding, documentation, coverage, or payer adjudication.
- Propose the appropriate coding, CDI, or validation change.
- Review and test the proposed change.
- Apply validated updates and monitor subsequent outcomes.
How CombineHealth Unifies Autonomous Medical Coding and CDI
CombineHealth is a self-learning autonomous medical coding platform with AI-powered CDI integrated directly into coding. It reviews complete encounters, identifies documentation gaps, generates or audits codes, applies configured payer requirements, and explains the evidence behind each decision. Supported encounters proceed autonomously, while exceptions are routed for review.
CombineHealth brings four capabilities into one connected workflow.
1. Autonomous coding with integrated CDI
CombineHealth evaluates diagnoses, procedures, E/M levels, modifiers, documentation sufficiency, and medical necessity during coding.
Rather than sending every encounter through separate coding and CDI queues, the platform identifies documentation issues as part of its coding process.
2. Configurable CDI workflows
Organizations can configure how documentation findings are handled.
Supported encounters can be finalized, lower-risk CDI alerts tracked for provider education, and cases requiring material clarification routed for review.
This allows organizations to apply specialty-specific and operational requirements without interrupting every claim.
3. Explainable coding and audit mode
CombineHealth links coding recommendations to the clinical evidence and applicable guidelines supporting them.
The platform can also operate in audit mode, reviewing codes generated by providers, EHRs, or existing coding systems for unsupported selections, missed opportunities, and documentation gaps.
4. Self-learning payer intelligence
CombineHealth’s payer intelligence analyzes denials, reimbursements, and underpayments to identify recurring payer-specific patterns.
Validated findings can inform future coding, CDI, and pre-bill checks, connecting documentation quality to downstream reimbursement outcomes.
Production Validation: Brault
CombineHealth's autonomous coding was evaluated through parallel production coding with Brault after a previous autonomous coding implementation failed to meet expectations.
The reported validation results included:
Brault also reported stable turnaround times below 12 hours during volume spikes and approximately two-week new-site go-lives.
These results demonstrate reported coding performance across varied physician documentation and production workflows. They should not be interpreted as separate CDI performance measurements.
Read the Brault autonomous coding case study
Why Choose CombineHealth for Autonomous Medical Coding and CDI?
Accurate coding requires complete documentation. CombineHealth integrates autonomous medical coding, CDI, and payer intelligence to identify documentation gaps, improve coding decisions, and prevent denials.
At a 400-bed hospital, CombineHealth helped reduce coding-related denials by 75%, identify 5× more CDI opportunities, and increase captured revenue by 4%.
Book a Demo to see how CombineHealth connects coding and CDI in one workflow.
FAQs
Can autonomous medical coding work without CDI?
Yes. Autonomous coding can assign codes from available documentation, but incomplete records may limit coding specificity or completeness. Integrated CDI identifies documentation deficiencies during coding and helps determine whether clarification is required before finalizing the encounter.
Is CDI the same as autonomous medical coding?
No. Autonomous coding assigns codes based on documented diagnoses and services. CDI evaluates whether the documentation accurately and completely represents the care delivered. Integrating them allows documentation sufficiency and coding decisions to be evaluated together.
Can CombineHealth audit existing EHR-generated codes?
Yes. CombineHealth supports an audit workflow that evaluates existing codes against clinical documentation and applicable requirements. It can identify unsupported selections, potential missed coding opportunities, and documentation gaps without requiring organizations to replace their existing coding process.
How does CombineHealth integrate CDI into autonomous medical coding?
CombineHealth evaluates documentation completeness during autonomous coding rather than treating CDI as a separate process. It identifies missing or conflicting clinical information, applies coding guidelines, and determines whether an encounter can proceed or requires clarification before finalizing the coding decision.